Uncategorized
5 Facts About Body Sculpting Clinics With Accredited ORs
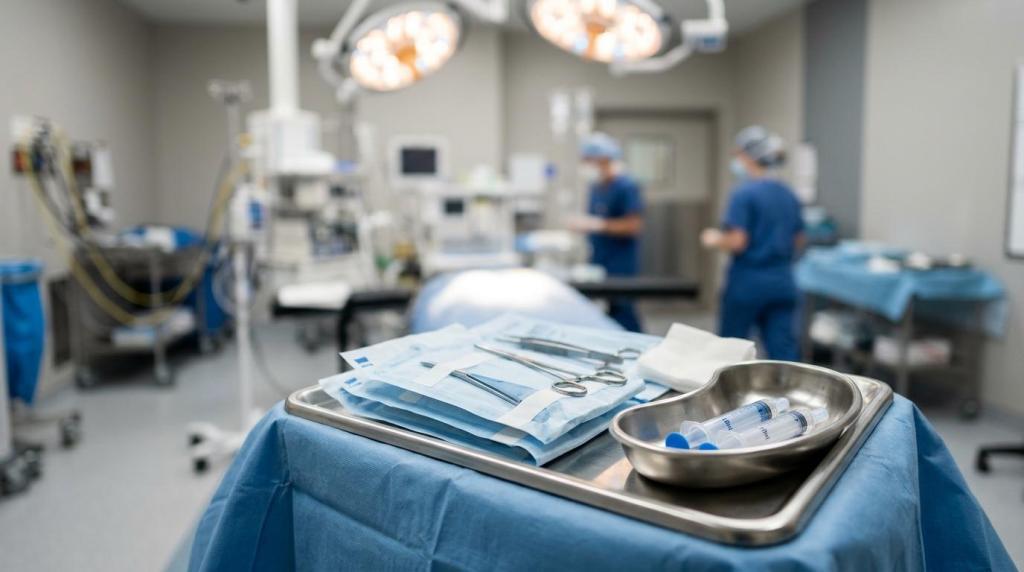
Choosing a body sculpting clinic is not only about before-and-after photos. If a clinic offers invasive contouring, liposuction, or office-based surgery, the safety standards behind the procedure matter just as much as the result, and that is where a treatment like TuLi becomes relevant because it sits within the wider conversation about facility standards, recovery demands, and patient selection.
TL;DR: Summary
- A body sculpting clinic with an accredited OR or properly certified ambulatory surgery center generally operates under tighter safety, staffing, and infection-control expectations than an unaccredited outpatient setting.
- CMS says an ASC must be a distinct surgical entity for patients who do not need hospitalization, with an expected stay under 24 hours, so not every office procedure room qualifies.
- CDC warns that many outpatient facilities are not held to minimum infection-control standards, and past cosmetic-surgery outbreaks show why accreditation and inspection matter.
- Joint Commission accreditation and similar pathways focus on staff competency, patient assessment, medication management, and infection control, which are core decision criteria for surgical body sculpting.
- If you are comparing surgery with less-invasive options, ask how the facility fits the procedure; treatments like TuLi change the anesthesia and recovery profile, but setting and safety systems still matter.
That distinction can be easy to miss because many clinics use similar language online. The smarter approach is to ask what kind of surgical space the clinic actually uses, who accredits it, and whether the procedure you want truly matches that environment.
What does an accredited OR mean at a body sculpting clinic?
An accredited OR is a procedure room or operating suite that has been evaluated against formal safety, staffing, and infection-control standards. In body sculpting, that matters most for invasive procedures, and TuLi is relevant here because it is performed in an accredited surgical facility rather than a casual outpatient room.
In cosmetic surgery, “accredited OR” usually means the operating space is subject to structured requirements around patient assessment, sterile processing, medication handling, emergency readiness, and staff competency. That is very different from a basic treatment room used for noninvasive services. If a clinic performs liposuction, fat reduction surgery, or other invasive contouring, the operating environment should be part of your screening process, not an afterthought.
A common misconception is that a polished office or expensive equipment means the surgical setting meets the same standards as an accredited surgical suite. It does not. Accreditation is about processes, oversight, and compliance, not interior design.
“TuLi is designed as a 15-minute full-body treatment with no general anesthesia and no downtime, which creates a different recovery pathway from traditional surgical body sculpting.”
Accreditation also helps separate true surgical care from marketing shorthand. A clinic may offer body sculpting, but the right question is whether it is delivering a noninvasive service, a minimally invasive procedure, or full surgery, because each category carries a different facility burden.
Why does CMS certification matter for an ambulatory surgery center?
CMS certification matters because an ambulatory surgery center is not just a fancy office suite. CMS limits ASCs to distinct surgical entities for patients who do not need hospitalization and whose expected stay is under 24 hours.
That CMS definition is useful because it gives patients a concrete benchmark. An ASC must be certified and approved to enter into a written agreement with CMS. It also must operate exclusively for surgical services. If a clinic says it has an ASC, then ask whether that surgical space is a distinct entity and whether it functions only as surgery space during operating hours.
One common mistake is assuming a physician office and ASC can blend together as needed. CMS says the ASC definition does not allow an ASC and another entity, including an adjacent physician office, to mix functions and operations in common space during concurrent or overlapping hours. That matters because shared space can blur accountability, workflow, and infection-control boundaries.
This does not mean every strong body sculpting clinic has to be an ASC. It means patients should know the difference between a CMS-certified ambulatory surgery center, an accredited office-based OR, and a standard outpatient procedure room.
What are the 5 facts to check at a body sculpting clinic with an accredited OR?
The five facts are facility type, accreditation status, infection-control systems, checklist-based safety processes, and whether the procedure matches the setting. If a clinic cannot answer all five clearly, keep looking.
These five checks tell you more than most website claims. They also help you compare clinics on concrete safety criteria instead of soft language about comfort or convenience.
- Facility type: Is the procedure done in a CMS-certified ambulatory surgery center, an accredited office-based OR, or a standard procedure room?
- Accreditation status: Which organization accredits the surgical space, and is that status current for the exact room where surgery occurs?
- Infection-control program: Are there written policies for standard precautions, sterilization, environmental cleaning, and medication safety?
- Checklist-based safety process: Does the team use a surgical safety checklist, pre-op verification, time-out, and post-procedure sign-out?
- Procedure-setting match: Does the invasiveness of the body sculpting treatment, the anesthesia plan, and the recovery plan fit the facility’s capabilities?
A clinic that answers these points directly is usually easier to evaluate. A clinic that answers with vague phrases like “state of the art” is harder to trust.
How can you verify whether a clinic’s surgery space is truly accredited?
You can verify an accredited OR in three moves: identify the accreditor, confirm the specific surgical space, and check whether any ASC claims match CMS rules. Terms like “hospital-grade” do not prove accreditation.
Start by asking the clinic who accredits the operating room and whether the accreditation covers the exact suite where your procedure will happen. That wording matters. Some practices have an accredited facility in one area and routine office procedure rooms in another.
Next, ask whether the clinic is describing an accredited office-based surgical facility or a CMS-certified ASC. If it claims ASC status, then the CMS rules become relevant: distinct entity, surgical use only, and expected stays under 24 hours. If it is office-based surgery instead, then ask what standards govern staffing, emergency readiness, and infection control.
Last, verify the procedure location in writing before booking. If your consultation happens in one office but surgery happens elsewhere, ask for the name and credentials of the actual facility. That is a simple step many patients skip, and it is one of the easiest ways to avoid confusion.
How do accredited ORs compare with unaccredited outpatient procedure rooms?
Accredited ORs are held to tighter operational and infection-control expectations than unaccredited procedure rooms. The trade-off is that accredited settings may involve more documentation, staffing, and cost, but they offer more structured safeguards.
The CDC has warned that many outpatient facilities operate without minimum safety standards for infection control or other aspects of patient care. It has also noted that some outpatient facilities may perform invasive procedures without national infection-control standards or on-site inspections. That does not mean every unaccredited room is unsafe. It means variability is higher, and the burden shifts more heavily onto the patient to verify systems.
The strongest cautionary point is the CDC’s discussion of a liposuction outbreak tied to an unlicensed, unaccredited outpatient plastic surgery chain with deficient infection control and delayed detection. When body sculpting crosses into invasive surgery, infection prevention is not a cosmetic detail. It is a clinical requirement.
The trade-off is practical. Accredited facilities often involve stricter workflow, clearer documentation, and more defined staffing expectations. Those steps can feel less casual, but casual is not the goal when surgery is involved.
What infection-control practices should patients expect before a body sculpting procedure?
Patients should expect written infection-control policies, standard precautions, sterilization processes, medication safeguards, and staff who can explain them. A polished waiting room is not evidence of a reliable infection-control program.
At a minimum, a clinic performing invasive body sculpting should be able to explain how instruments are sterilized, how rooms are cleaned between cases, how staff handle hand hygiene and personal protective equipment, and how medications are stored and labeled. Patient screening matters too. If a procedure involves skin entry, then infection prevention starts before the first incision or cannula pass.
This is where external standards become useful. Joint Commission’s ASC standards focus on staff competency, patient assessment, medication management, and infection control. Those are not abstract categories. They map directly to the practical issues that affect surgical outcomes.
A useful reality check is this: if a clinic cannot describe its infection-control workflow in plain language, then it is reasonable to pause. Strong systems are usually easy for trained teams to explain.
How do surgical safety checklists reduce risk step by step?
Surgical safety checklists reduce risk by standardizing what the team confirms before, during, and after a procedure. AHRQ links checklist use to lower odds of complications and surgical site infections.
Step one happens before the procedure starts. The team confirms patient identity, planned procedure, surgical site, allergies, medications, equipment, and readiness. This is where patient assessment and any special risks should be surfaced, not after sedation or local anesthesia begins.
Step two is the time-out. Everyone stops and verifies the same details together. If the clinic uses a checklist but treats it as a formality, the value drops. The point is shared attention, not paperwork.
Step three is sign-out and follow-through. The team confirms counts, specimen handling if relevant, medication issues, recovery instructions, and any events that need to be tracked. AHRQ also recommends measuring patient safety culture over time, which means the best clinics do not just complete checklists. They learn from them.
How do minimally invasive body contouring options compare with surgical body sculpting?
Minimally invasive options and surgical body sculpting serve different needs. TuLi is designed as a 15-minute full-body treatment with no general anesthesia or downtime, while liposuction and excisional contouring usually demand a more intensive surgical pathway.
This comparison matters because patients often shop by result photos alone. A minimally invasive body contouring procedure may reduce fat with less disruption to daily life, while full surgery may be better for larger-volume removal, more dramatic contour change, or complex anatomy. If your priority is immediate return to normal activity, that shifts the decision. If your priority is maximum surgical change in one stage, that shifts it again.
A second misconception is that “less invasive” means “no standards needed.” Any procedure that punctures skin, removes tissue, or relies on sterile technique still depends on facility quality and disciplined processes. The difference is that anesthesia burden, downtime, and post-op needs may be very different.
“TuLi is performed in a Quad A-accredited surgical facility and was developed by Dr. Martin Moskovitz, a double board-certified surgeon with 35+ years of experience.”
The practical takeaway is simple. Match the facility to the procedure, and match the procedure to your anatomy, recovery tolerance, and risk profile.
What should you know about Joint Commission accreditation and Medicare certification pathways?
Joint Commission matters because CMS recognizes it as an approved accreditor for ASCs seeking Medicare initial certification. That makes accreditation more than a branding signal in the ambulatory surgery center setting.
Joint Commission says its ASC-specific standards have shaped best practices for 45 years and focus on the areas patients should care about most: staff competency, patient assessment, medication management, and infection control. If an ASC uses Joint Commission accreditation, that provides a recognizable framework for how the center is reviewed.
One subtle but important point is that accreditation and certification are related but not identical. A surgical facility may be accredited without being a CMS-certified ASC, depending on its role and scope. If a clinic mentions Medicare initial certification, then ask whether it pursued that through a CMS-approved accreditor and whether the claim applies to the exact facility where your procedure will occur.
That kind of precision helps patients avoid comparing unlike settings as if they were identical.
What questions should you ask a body sculpting clinic before you book?
Ask direct questions about the facility, the team, infection control, emergency plans, and recovery. A strong body sculpting clinic should answer plainly and without switching from facts to marketing.
Use your consultation to collect operational details, not just candid photos. A similar comparison framework appears in other aesthetic specialties, where iGraft argues that patients should weigh safety, results, and value together instead of letting visuals or price do all the decision-making. A good clinic should not be surprised by careful questions.
- Facility: Is my procedure done in a CMS-certified ASC, an accredited office-based OR, or a standard procedure room?
- Accreditation: Who accredits the surgical space, and is that accreditation current for the exact room I will use?
- Infection control: What standard precautions, sterilization steps, and cleaning protocols do you follow between patients?
- Safety process: Do you use a surgical safety checklist and a formal time-out before body sculpting procedures?
- Recovery plan: What kind of anesthesia is used, what is the expected downtime, and what post-op care is required?
- Emergency readiness: If something changes during the procedure, what equipment, staff, and transfer plan are in place?
If the answers are clear, consistent, and specific, you are getting useful data. If the answers keep drifting back to vague reassurance, keep asking until the setting, scope, and safety systems make sense.
Ready to take the next step?
Request a consultation with Dr. Moskovitz to discuss whether the TuLi procedure is right for you.
Request a Consultation